We’re not. We’re dead serious. We want to keep them alive.
Maybe you have a teen like the ones we see. Maybe you are are one… like the ones we see. Or maybe you’re quiet. Kind. Smart. Everybody’s friend. Absolutely gorgeous. An athlete. A contender. Someone who’s had it all. Or maybe you’re NOT any of that. Maybe you’re a worrier, shy, awkward. Maybe you feel like you’re always messing up, like no one wants to be with you, like no one knows how to help you. Like you’re lost. Like you just don’t get it. How everybody else is goofing around, laughing, having fun while you just sit there, wondering how it ever happened that things got so screwed up, and that you got so messed up. Know anybody like that? If you do, or if that is you–or your teen, or your sister, or your best friend–listen up. You’re in the right place. Because there is IV ketamine for teens.
Just when you think that nothing can help, know that we have help. We have the experience, and the guts and the compassion–and we had the foresight–to see the potential that ketamine infusions could offer adolescents who are just suffering.
We knew it years ago, when we first started using IV ketamine for treatment resistant depression. Then bipolar depression. Suicidal thoughts. We saw it, and decided to really look at what happened to real people (who always have 50 million things going on, not just one rarified condition or syndrome. We looked at our own patients, in our own practice. We wanted to look at our own numbers, the truth of who gets better, how many get better, what does it take– (in terms of ketamine) — how much? how often?
We stepped up, powered up, and wrote up a critical research report and published it in a peer reviewed journal about what happens for patients who come to see a psychiatrist to see if ketamine treatment can help–for their depression, it was back then–and find that it can stop hopelessness and suicidal thinking in an afternoon.
The thing is, we saw years ago it could help adolescents… Adolescents who weren’t just needing to take a pill to get better. These didn’t get better with one pill, or two…or a combination of several. And when they didn’t get better, it was said they had treatment resistant depression.
But treatment resistance is a funny thing. It used to be that it meant you’d tried 4 different meds, then it was dropped to 2 different meds, and now in this adolescent study, treatment resistance was defined as having been treated with one medication that didn’t work.
We’re glad that the requirement was just one failed medication trial before they were given the opportunity to be treated with IV ketamine.
Why?
Because so much is happening in a teen’s life and it’s happening so fast. They’re rate of growth is so intense that a day, a week, a month, of loss causes too much loss. And when there is no resolution found, time can fly by in years, and a teen loses a major block of development they never can get back.
IV ketamine for teens to put a stop to loss.
So what losses can they afford? To miss a month…or a semester…of high school? Or college?? To drop out of basketball? Lose friends? Teens often don’t have the patience and tenacity for a friend who just doesn’t show up. Or one who is always down. Defeated.
Adolescents need action. They need solutions that work quickly. They don’t have the time to wait for 4 different medicine trials that go on for weeks or months. There is just too much loss.
That’s why IV ketamine is so important.
When there’s no time to lose this is something that works fast.
How much can your kid afford to lose …how much can you afford to lose?
Hopefully we’ll able to have more and more data coming out so that our kids won’t have to suffer so long… so they get better faster. So we can treat them with what is most likely to work before trying something first that probably won’t.
We do the best we know in this profession. But we need more studies and more information. And until we have it…well, like I said, we do the best we know.
And we know this treatment has been in use to help adults of all ages for years. But what if you’re a teen? Teens get depressed, suffer social anxiety, even suffer from PTSD,suicidal thoughts, and bipolar depression. And when it’s treatment resistant, the unrelenting symptoms can interfere with your life, your development, and your hope. So we step forward and reach for IV ketamine for teens.
A study was just published about treating these kids with IV ketamine, to see if it was truly effective and safe…more about that coming up. But get this:
76% of this study group below had relief within 3 days of the ketamine infusion!
Imagine what that would mean to a teen who’s suffering, hopeless, and giving up.
So IV ketamine treatment has been effective in smashing those symptoms in thousands of people. But let’s look at this study especially for adolescents:
IV Ketamine for Teens
A team of researchers at Yale University led by Jennifer Dwyer, M.D., conducted a 4-week study using IV ketamine in teens with treatment-resistant depression recently published in the American Journal of Psychiatry. They selected 17 adolescents ages 13 to 17 who had been diagnosed with major depressive disorder, or MDD.
It’s a massive undertaking to find kids that don’t have 6 different things going on with them… a cluster of co-morbidities. Teens who have just one diagnosis are the only ones that fit into a study like this. Just finding the subjects for a study is hard.
Each teen in the group had been failed by at least 1 antidepressant medication treatment, but overall the average of failed treatments among the group was 3.24. (That’s a lot!–a lot of trials, a lot of weeks and months waiting for medications to help and being disappointed when they didn’t.) The average length of the current depression episode for these teens was 21 months. Almost two years. Too long.
This crossover study gave each teenager either IV ketamine 0.5mg/kg over 40mins, or IV midazolam 0.045mg/kg over 40 mins.
Then 2 weeks later, each teen received an infusion of the other medicine.
It’s important to understand that midazolam (which is from the Valium family) is often used as the “placebo” tested against ketamine because it provides an experience of deep relaxation, so at low doses it can be a bit difficult for the subjects to know which one they’re receiving. (Often, though, there are little clues and little differences between them so that they can tell.) But midazolam provides no antidepressant benefits.
It turned out that 76% of the adolescents experienced at least a 50% or greater antidepressant response within 3 days following their ketamine infusion. (Compare this for a second: with an oral antidepressant, only 35% get 50% better….after 6-8 weeks.)
Were there side effects during the infusion in the study? Of course. But minor. For example, adolescents who had received ketamine experienced an increase in blood pressure compared to the midazolam infusion, but within a few hours those effects subsided.
Oh, the beauty of it.
When you’ve struggled and hidden in sullen isolation, sometimes for years… and you don’t know whether to search for a solution or hide, it’s so darn hard. You’ve missed class, missed practice…because it was too hard.
Until something happens… and you realize you only seem mad at others — and the world — because you feel so terrible.
Because you’re depressed.
And you also may be laboring under the weight of other disorders as well, like trauma, PTSD, OCD or social anxiety…ugghhhh. When all of these different symptoms or disorders cluster and tangle together, it’s so much harder to find relief.
Then, after months or years of searching for help, you learn about IV ketamine treatment.
And you come back to yourself after treatment. Older and a bit wiser maybe, but joyful and creative again. Able to love again.
This is the beautiful story about how IV ketamine can transform adolescents…and can restore their hope.
For years, the use of ketamine treatment was up in the air. Respected doctors and neuroscientists were quick to offer their professional opinion… which was to wait. They said that ketamine had not been researched enough. There was not enough information to back it up…so they said.
But now we know that IV ketamine can transform adolescents, adults, and even children. It can erase suicidal thoughts, and give you … a teen… the time you need to get the help you need to see things differently. To redefine what life can be for you. To rebuild your hope. You purpose. And to restore the energy you need to build friendships that are strong and healthy.
We’ve waited a looong long time. Too long for some adolescents…
Even though we need more studies and more questions answered, we have to be willing to step up and take care of our kids who have everything on the line. For them it could be a matter of hope vs despair…life and death.
We live on that line all the time.
For all of us. We choose life. We need to choose it for our kids, too.
At Innovative Psychiatry, we find great joy in watching young promising people like you — who come to us without hope or confidence — tell us enthusiastically after their treatment how good they feel and how their life is getting better and better.
And because this process, this treatment, is so important, we took steps to make our office a safe place for you. We have technology that destroys viruses and all kinds of germs in the air and on surfaces, so you can feel safe and protected from infection of any kind. Whether it’s COVID-19 or influenza, or strep…it all dies immediately. So you can be in the safest possible environment during this pandemic and focus on your treatment and getting better.
If you’re an adolescent with symptoms of depression or anger, if you have tried antidepressants that haven’t helped, ask your Mom or Dad or someone who cares about you to call us.
We want you to find your joy again. To find your freedom and your hope.
We’re all weary of hearing about COVID and mask wearing precautions. Aren’t we?
About the negative impact of isolation. And while we see improvement on the horizon through wide spread vaccinations, there are still imminent risks, and new cases as well as deaths every day. Those risks add to your daily stress in ways you may not realize. Pandemic anxiety depletes your bandwidth for coping with daily living. The story of Carolee and Jacob illuminates the kinds of stressors that can go on behind closed doors…
Carolee and Jacob walked the two blocks to the grocery story to pick up food for dinner. They were discussing a news story they’d read on the internet about how some states are lifting mandates for COVID precautions, like wearing masks, social distancing, and use of hand sanitizer. They liked walking to their neighborhood store when they could, just for fresh air and exercise.
Since they passed a number of people on the sidewalk as they walked, they always wore masks, even when they were outside.
Carolee expressed her frustration that those particular states were lifting the requirements, in spite of the fact that each governor had strongly encouraged citizens to continue to use precautions on their own.
Of course, there will be those who step up and “discipline themselves” and maintain the precautions. But she knew there would be so many… so so many…who would not. Her frustration and disgust exploded.
“WHY????? Why would they drop this requirement before we’re ready for it? People aren’t going to do the right thing. They’re going to just be glad to be rid of it all and do what they want to do for fun! And the cases will start growing…and more will die… and….”
You Can’t Control Everyone… Just Yourself, Right?
Jacob squeezed her hand and tried to soothe her. “Carolee, you know there are already so many who don’t follow the rules. But you and I can only do what’s best for us…Don’t you think it’s futile to struggle about everyone else, when it’s something we have no control over? It’s really not worth you getting wound up and shaken about something you can’t control…is it?
“It’s about bandwidth, Carolee. The amount of information your brain can receive…like per second. We’re flooded with so much more to consider about every detail of life than we’ve ever had to. This pandemic anxiety depletes the bandwidth we need just to get through every minute, every hour. We have to find ways to tamp down our own response to things, so we have more energy for everything else.”
Jacob knew that Carolee hadn’t been sleeping well lately. She seemed to wake up frequently, sometimes walking through the house wringing her hands. Sometimes just pacing. Staring out the window. Standing out on the patio.
They’d talked several times about how the COVID-19 variants were spreading, asking questions about whether the new vaccines would be effective with the variants… About how long they were waiting on the list to get their own vaccines. Each time they talked, they agreed to let it go, for their own peace of mind.
But that was easier said than done.
To make matters worse, Jacob was feeling more and more worn down by the stress of the pandemic, his work responsibilities, and Carolee’s meltdowns. He knew she would get past them, but he found himself worrying about her more and more. He needed to find a way to relax. In addition to Carolee, Jacob sure needed some relief.
Worry. Worry. Then worry some more.
Life was already full when COVID-19 came along. People were already stressed with daily responsibilities to job, family, faith organizations, maintenance of home and car, children and their struggles.
When the pandemic appeared on the horizon like a vast dark cloud of pestilence, it pervaded everything. Those aspects of life that were so routine and required little attention, came to require acute attention often overloaded with a sense of panic with fear of doing it wrong.
A psychiatrist wrote in Psychiatric Times about the fear and guilt she experienced when she stopped by the bank for cash only to find the drive-through banking not yet open. So she wrestled with herself about whether to go inside the lobby or park and wait an hour for the drive-through to open. She went inside, but worried about whether she had been exposed to COVID-19 and who she might expose through the day as a result. She worried about it all far more than she normally would have.
Kate Murphy, a NYT journalist, made the point that your brain is overburdened by this pandemic. That things you normally relegate to your brain’s autopilot now require serious thought and risk analysis. And…as a result, you have less bandwidth for higher order thinking.
Less bandwidth.
Isn’t it true?
And those pandemic anxiety reactions eat up bandwidth.
If you’ve depleted yourself through a panicky reaction to forgetting your mask when you MUST buy groceries, or driving through for a meal but your hand sanitizer is empty…how can you eat without sanitizing your hands?? Or you’re trying to cope with working from home and the kids are jumping out of their skins from cabin fever??
What do you do when you keep hitting your thumb with a hammer?
Those bandwidth-eating reactions are similar to hitting your thumb with a hammer, over and over and over… because more and more damage is done. You can hardly cope with everything else when your thumb is screaming in pain, you know? You just have to step away from the hammer!!
Then, if you’ve already been taking medication for anxiety, and the exponential expansion of anxiety caused by the pandemic sends your worry and panic through the roof, well, you have difficulties you hardly know how to manage.
There was a time before the pandemic was anticipated, that worrying about little things blew up into worrying about disasters in your mind, and as your grandma would say, “Honey, you’re borrowing trouble and making a mountain out of a molehill.”
But now, the ongoing stream of changes and increased risks you face everyday can result in outright panic for some, and on a lesser scale, confusion and exhaustion…and dread. This pandemic anxiety just depletes your bandwidth for life.
You probably know people who have contracted COVID-19. You may have seen some who experienced extremely mild symptoms, if any at all. Still, you may also know someone who experienced serious or extremely severe symptoms. Maybe you know people who have died.
If you’ve known more than 1 person who has died, your anxiety about death may have filled you with alarm. Alarm about masks, about social distancing, about making sure OTHERS are doing what they’re supposed to be doing.
And what’s more upsetting than people who won’t comply?? You just have to step away from that hammer…
The more traumatic your experience has been, the more anxiety you may feel about the risks. On the other hand, if you have not known anyone who was hospitalized from COVID-19, exposure may not seem like a great risk to you at all.
Either way, you need to be grounded. To let the world take care of the big solutions while you manage the challenges of your daily life. To help with that, take daily walks – wearing your mask! — but get out in the fresh air and sunshine. Take a friend or family member along and talk. Take care of YOU. Then look after your family.
Pandemic anxiety depletes your bandwidth for your own life. Right now, you need all the energy and mental clarity you can get just to get through life, day by day.
Since IV ketamine treatment is at the front lines transforming people when nothing else has helped, it may be an obvious next step for you. And receiving these infusions is a relaxing and comfortable experience. With your remission as our goal, your dose will be titrated according to your individual response during each infusion.
At Innovative Psychiatry, we’re working every day to respond to the call for helping people who are against the wall in this pandemic. If your own bandwidth for coping with the demands of COVID on top of the demands of your life is growing slim, you’re not alone. A vast mob of stressed out, overwhelmed, exhausted, and depressed people surround you. You have to decide what to do about it, if your efforts toward exercise, fresh air, and medication have become futile.
In that process, it could be that the results of stress have depleted your ability to cope anymore. You may need to reboot. You may need a remodeling project in your synapses to increase your synaptic plasticity. To relieve your symptoms of depression, PTSD, or suicidal thinking. To give you fresh bandwidth.
For your safety, we’ve installed state-of-the-art technology that utterly removes and destroys COVID-19 and viruses and pathogens from the air and surfaces. So you don’t have to spend bandwidth on your safety, when getting treated is so important for you. Just one more thing to lighten your load. You have enough on your mind.
If this sounds like you, and you’d like to discuss IV ketamine treatment, call us.
This pandemic has been hard for everyone. You’re not alone. And we’re here to help.
We look forward to talking with you and working together for your relief.
You may hear people say, “Antidepressants and other psych meds just don’t doanything…”
Some people say, “…placebos work better…” Oh please. But why do they say that? Maybe their own experience with prescribed medicines was disappointing. So — of course — they’re disillusioned about these medicines. We get it. And we know that any given medicine that works for some people won’t help some others at all, or might even make them worse. Sooo… what’s up with that? Well, the answer isn’t simple. We do know that antidepressants,when first prescribed, only help about 30% of depressed people. We know that psych drugs help some people but not others and that men and women can experience depression and anxiety and fear differently. It’s a tangle to unravel it all. That’s why we’re so excited about new developments. We want to keep your eyes on AKT because it might explain how we learn and forget fear.
Meet Jill and Greg to see how differences affect their well being and livelihood:
Jill and Greg own a coffee shop together and are partners in life as well. They have a great balance of power, in the tasks they divide between them and the strengths they each bring. Greg is a people person, creative, funny, and efficient at both designing new drinks and training staff to make them just right. Jill is a numbers person, and sometimes comes off a little stiff and awkward, because she just doesn’t have Greg’s gift for setting people at ease. She also has some social anxiety going on.
She does ordering from suppliers, closes out the books every night, and keeps a close eye on profit and loss. They’re a perfectly matched pair and love working together. That is, as long as they’re both at their best. With Greg building relationships with customers and vendors, and Jill keeping the financial end sound, they really do provide strength for the weakness of the other.
Unfortunately, they both suffer from disorders that periodically causes some lost time at the shop. When that happens, the one who is doing OK ends up carrying a double load. And both of them struggle with anxiety… or basically fear on some level.
Greg was diagnosed with bipolar II disorder when he was a teenager. Jill was diagnosed with depression in college. She’s a worrier. He just explodes sometimes—and refuses to call it anxiety. Greg takes medication for mood stability that also has an antidepressant effect. Jill takes an antidepressant that only sort of works. They probably both need medicines that reduce anxiety.
In a perfect world…
Since their coffee shop venture requires all hands on deck to run smoothly, Jill and Greg are eager to find the right meds for both of them to help stay in the game. They need to be able to go in to work—they can’t afford not to. It seems to Greg that since his medication helps him as much as it does, Jill should ask her doctor to prescribe the same for her. She’s a nervous wreck! However, she knows enough about changing meds that she can’t just jump on another medication just because it works for Greg. She’s tried that before. It didn’t work.
At this point, Jill has tried five different antidepressants over the past few years, and has researched enough about IV ketamine treatment that she wants to talk to her doctor about whether she’s a candidate for it.
Considering something new takes a little bit of courage. She wasn’t sure what her psychiatrist would say. A visit with her psychiatrist surprised her–he was cautious but supported her trying something that might help. Jill decided to pay for it out of savings, because her bouts of severe depression were taking a toll on the shop and their income.
She arranged for treatment and began infusions. When the treatment was complete, she had received 8 infusions over about 3 weeks, and she felt like she had a new lease on life. Her ketamine infusions seemed to wake up her brain. And that got better and better day by day — even after she completed treatment. She found she enjoyed singing and dancing, and painting became her new passion. When they had a problem in the shop, she had so many more ideas for solving it. Working on the book work was no longer a drudgery–she enjoyed it and got more accomplished in a shorter time.
Jill and Greg’s life became so much better at work and at play. Greg still had slumps when his meds weren’t quite holding him, but their life was so much better overall. They had read that ketamine treatment could help bipolar depression, too. Maybe the next time he went through a bad bout of that, Greg would talk to his doctor about it. To see if it was right for him—not just to copy Jill.
Finding the right medicine for you is sometimes a long search. And medicine that works for you may not work for your sister…or your son. But it’s well worth the work researchers do to better understand why.
A research study at the University of Colorado Boulder offers one fascinating revelation about why those differences between people and genders might exist.
It has to do with a key protein kinase in the brain called AKT…which functions differently between males and females.
They found presence of a certain form of AKT (called an isoform) in male mice can help the male let go of fear from a past painful experience–and form a new adaptive response to get around the old fear. Wait, what? Doesn’t that remind you of the way synaptic plasticity helps you adapt?
Ok, you’re right…mice aren’t people and it doesn’t work quite that way…. but AKT is remarkably similar across mice and humans and this kind of translational research can begin to give us specific information to make our medicines and medical care more specific. Potentially even gender specific.
So you’ll do well to keep your eye on AKT because so much is being learned about how we learn and how we forget fear.
By figuring out the very complicated cascades involved in creating synaptic plasticity, we may be on the verge of figuring out how to shape and foster the neuroplasticity–for the better.
We may be able to personalize medication therapies so that they don’t just broadly address a disease state, but so that they can be specific for the man or woman who needs them.
Charles Hoeffer, the principal investigator of this study, said it like this: “We need to stop hitting every ‘disorder’ with the same hammer.” Well said! (Wish I had said that!)
We’re always talking about personalizing treatment. About how important it is to provide treatment that fits the individual. Just as that’s true with all of the fine details involved in ketamine treatment, it’s also true with all of the medicines we prescribe.
So… about AKT.
It turns out AKT plays a lead role in synaptic plasticity. We’ve talked about that too… The idea that the connections between cells in the brain can change and adapt. They can change and adapt as a result of an experience. (This is why trauma can change us.) But — so importantly — these connections can also grow, change, and adapt as a result of the deeply emotional experiences, like the incredibly deep and awe-filled experiences you can have during a ketamine infusion. So many of our patients do. We’ve talked about how taking advantage of that process by scheduling psychotherapy 24 hours after a ketamine infusion can enhance the effectiveness of the infusion.
Why? Because therapy helps you think differently about something…and synaptic plasticity empowers those changes in thought. Many of our patients also find that journalling, creative writing, meditation and other activities help to integrate those experiences into their lives, find meaning in the experience, and move forward. Keep your eyes on AKT… there’s so much more to learn.
AKT helps you create memories. Like a child touching his hand to a hot stove. To encode that memory so that he will be cautious in the future around hot burners, his brain needs to activate protein kinases like AKT.
In fact, AKT is one of the first proteins to present itself to form a memory like that.
There are 3 main variants, or isoforms, of AKT and they do different things and affect people in different ways (More on that in a sec!)
AKT1 is important in encoding new experiences and allowing you to forget the old.
AKT2 is often found in the astroglia…which are star-shaped brain cells.
AKT3 seems to be important in brain growth and development. This one plays a positive role in mental health and wellbeing.
And when AKT1 and AKT2 are working together in the prefrontal cortex, they’re vital for learning, for memory … for dynamic change.
Maybe like the kind of dynamic change that you want for yourself. So yes. So many different forms, working singly and sometimes together, in ways we are only now just beginning to understand for people suffering with psychiatric disorders.
Now. To add another twist to this picture. In this study, researchers found a dramatic difference between genders regarding AKT.
They found that male laboratory animals whose AKT1 was functioning well, had far more ability to replace unwanted memories with new ones…than those who were missing AKT1.
Draw that out for a moment now…. and imagine men who’ve experienced the trauma of illness, or assault, or combat… and imagine for a moment that they’re given the opportunity to experience something new — maybe hopeful, blissful, awe-filled, like they might during a ketamine infusion — and then the excitement of realizing that a tiny little protein kinase like AKT1 may play a part in helping to encode that new feeling. Turn it into a new memory. Make the old traumas fade. (That’s called extinction learning.) Teeny little AKT1 helps with this. In males.
Incredible.
There are endless little nuances in your brain that translate your experiences, encode them, and shape your synapses…and your individual functioning. And maybe your future possibilities.
(Let’s just say we read all this stuff for fun–at nights, on the weekends, and at 5 am with a double shot of espresso.)
And at this point, serial titrated IV ketamine infusionsstill do the best job we’ve seen in bringing relief to more people with treatment-resistant depression and anxiety than just about anything else available today.
But ketamine treatment doesn’t work for absolutely everyone. Is it because of AKT or something different? We don’t know. Not yet. Researchers like the ones at Boulder are still searching to understand the nuances of dendritic growth and synaptic plasticity in order to refine our treatments–and discover better ones.
At Innovative Psychiatry, we personalize treatment to fit you — all the complexity and all the wonderfulness of you! And we aim for remission. Not just response. That’s the reason we titrate your dose, duration of the infusion, and the number of infusions you need to help you discover — once again — your best self.
When you struggle and suffer from the symptoms of disorders that can be tormenting and exhausting, getting treatment is paramount. And feeling safe is critical — so we have state-of-the-art technology that crushes 99.999% of all viruses and pathogens. During this pandemic we want to make things easy. We all need a little bit of easy.
This is National Eating Disorder Awareness Week — NEDAwareness Week
People come in a wide variety, don’t they? No one more deserving than another. Whether there are differences in skin color, differences in gender, differences in sexual orientation, differences in religion…or differences in IDEAS. And no matter the differences, no matter the variety, every body deserves a seat at the table. We may speak of the table as a place to eat, or we may speak of the table as a place to exchange ideas. It happens that this week we’re talking about both. Because we want to think about how NEW ideas and NEW approaches can bring NEW FREEDOM to people with eating disorders.
An eating disorder causes you to see food and yourself in a distorted way. A way that affects you both physically and mentally. That distortion creates distorted eating patterns. And those eating patterns can cause damage to your body and your mind… as well as your life expectancy. And of all the eating disorders, anorexia nervosa is the most dangerous. With its poor response to treatment, such persistence, such rigidity. It takes over. It’s exhausting. We need more effective treatment for anorexia.
Eating disorders affect 32 million Americans. Twice as many women as men. Whether it’s bulimia, binge eating, anorexia nervosa, avoidant/restrictive eating disorder, or others, the need to raise awareness for support, education, and especially effective treatment, is paramount.
And although we hate bad news, there’s more bad news. The death rate in women with anorexia is 10 times greater than in other women. One major reason is that the metabolic and medical problems caused by self-starvation can be critical, even fatal. And also because the desperation triggered by anorexia can lead to suicide… and often does.
So let’s talk about what an eating disorder is…and what it isn’t.
In general, a variety of biological, psychological, and sociocultural factors tangle together and lead to a disorder of this type.
The idea that eating disorders are a “girl’s disease” a disorder where a girl seeks her parents’ approval is false. Archaic. Fiction. Can you say Old Wives’ Tale?? Similar to some other diseases, there is a biological basis for anorexia — and genetic studies identifying the first 8 genetic loci! — that is exacerbated by sociocultural and psychological/psychiatric components.
And, by the way, let’s square off against the idea that eating disorders aren’t serious. They can, and often do, wreak havoc on you and the people who love you. They can interfere with your relationships, your livelihood, and your own sense of peace and self-respect. And they can tear down your health.
We need to up our game if we want to erase this hold they have on us, and erase the shame and stigma they carry. We need to up our game if we want to make headway in treating the most deadly of these disorders — anorexia nervosa.
Anorexia has the highest mortality rate of any psychiatric illness. (Or it did, until the opioid crisis recently claimed the lives of so many.) That mortality is caused by the medical consequences of binge eating, purging, starvation, over-exercising. And these consequences include heart attack, kidney failure, osteoporosis, electrolyte imbalance… and suicide.
Because of the stigma attached to eating disorders, early diagnosis can be hard to achieve. And early diagnosis is important for effective treatment. Because these disorders can begin at any age. And last for years
…and let’s get One Thing Straight Now:
Eating disorders are NOT a matter of choice. They’re diseases governed by physiology and biology, with genetic, social, cultural, and psychological factors. Help remove the stigma associated with eating disorders, to make the world a safer place for everyone… because every body deserves a seat at the table.
Stigma comes from ignorance. It’s the inclination to pour shame on anything not understood. And that shame can be crippling. It can force someone who suffers into hiding…isolation… when it’s light, enlightenment, and help that is so deeply needed.
When you’ve been isolated in the throes of shame, (and you know you haven’t done anything to deserve it!) it’s hard…really hard...to come out. Sometimes it’s hard just coming outdoors, for Pete’s sake! But sometimes, it’s coming out with truth about yourself. About your sexual orientation, about your habits, or about the way you think…or eat. It makes you feel vulnerable… and like you’re making yourself a target for hatred, stigma, and judgment.
Sometimes eating disorders live silently inside— and sometimes they can’t help but show themselves, and then the anguish, the anger, the frustration, and the way they take over your life becomes…unbearable. And stigma or not, you realize you just have to find help.
And especially, if you suffer from Anorexia Nervosa.
There is plenty of stigma about anorexia… and you may hear people toss the term around disrespectfully, because they don’t grasp the critical nature of the disease. If they suffered from it themselves, they would not speak hateful words in ignorance, because they, too, would be informed. But that’s the nature of the beast of stigma, isn’t it?
The death rate in women with anorexia is 10 times the death rate in those who don’t suffer from it. But every body deserves a seat at the table, a chance to live well… and not die from the critical medical conditions caused by self-starvation.
And again, remember that this self-starvation is not by choice, but is associated with genetic factors, and fueled by changes in the brain that happen in some women and men when they start to lose weight, get energized, and begin to exercise compulsively. And we recognize that there are a host of other factors that can contribute to a slow spiral, a continuous weight lose, the emergence of anxiety, fear, and rigid rules.
But sadly, the most distinctive and cruel of the symptoms of anorexia is the “anorexia voice.” A voice talking to you, controlling you, commanding you, every minute of every day, telling you what to eat, what not to eat, when to exercise, when to feel guilty, and on and on and on it goes.
Treatment is effective only when “the voice” can be silenced, and you are free to make choices you want to make. About food, about love, about activity… about hope.
So what can be done?
Sometimes if you have a new idea, it takes courage to offer it up — like Conflict Zone: A Play on Eating Disorder Recovery, a live-streamed one woman show with a compelling storyline about the lived experience of recovering from an eating disorder kicking off NEDAwareness Week — but it could be brilliant. It could deeply resonate. It could breed a whole new movement fueled by hope.
And while it may draw stigma and resistance from those who don’t understand the idea, those who need what the idea could provide grab onto that thread of hope.
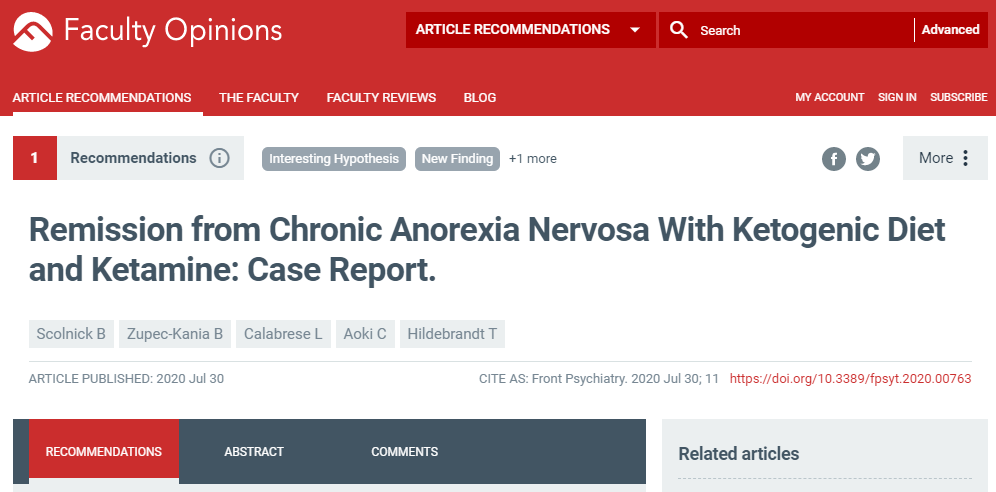
We’ve had the opportunity to work with a few other researchers to write up and publish a case report that incorporated a specially designed modified ketogenic diet combined with ketamine infusions that resulted in complete remission of severe and enduring anorexia in a 29-year old woman who had been ill for 15 years. Striking. Striking that her remission is complete and sustained and has persisted now for over a year. (See our blog about Caroline).
The case report has taken off, generated a lot of interest (and a lot of controversy — as you might guess when we put a ketogenic diet and ketamine on the table). It’s nice to see the metrics climb, the interest rise, to see the hope bud in people with anorexia who’ve lost hope of ever beating it… and to see the sparks fly in the imagination of the scientists, doctors, therapists and dietitians who try to help them. Our case report was recommended by Drs. Miletta and Horvath in Faculty Opinions as a New Finding, Interesting Hypothesis and Technical Advance, and written up in a lovely Faculty Opinions blog.
So… we’re now following up with a small clinical trial involving more subjects which is registered on ClinicalTrials.gov. Because we need an N greater than 1. We need to see if what worked will work for more people with chronic anorexia. This next step will give us more information about the effectiveness of our new sequenced approach in the treatment of anorexia.
As you can imagine, we’re cautiously excited to see what we can learn. And we’re hoping to see more and more studies to support novel treatments for anorexia.
At Innovative Psychiatry, we’re so pleased to see people with severe treatment resistant depression, bipolar depression, social anxiety, PTSD, and suicidal thoughts achieve remission with serial titrated ketamine infusions.
When you consider that the first paper published using ketamine for the treatment of a psychiatric disorder was using ketamine infusions for the treatment of anorexia — unbelievable but true!– more than 20 years ago, it’s WAY past time for people with anorexia to have truly effective treatment options to help them achieve remission. Every body deserves a seat at the table.
As our clinical trial launches, we remain right here, in the office, with boots on the ground, and continue to treat all of our patients for the symptoms that interfere with their lives.
We work to help you get the treatment that will help you with your symptoms and give you the freedom to live a rewarding life. In addition, we also work with our colleagues over the phone, email, and at conferences to learn all we can to better help you find remission. And, we pursue research opportunities to increase the medical knowledge available to all of us. For you.
Because every body deserves a seat at the table, including you!
We want to see you build a fulfilling life. That’s our heart in all we do.
See the Faculty Opinions and Recommendations featured in Faculty OpinionsHERE
Our work was was also featured in Faculty Opinions Blog — such a great piece with wonderful interviews with Barbara Scolnick MD and Caroline! Jump in and read it HERE
Read our full case report in Frontiers in PsychiatryHERE
Turns Out Winter 2021 Hasn’t Run Out of Stressors to Throw at You Yet…
People like you have been finding ways to adapt and endure this historical and very strange year. Never think that major factors in society, and in science, and in government, have no effect on you and your personal life. In fact, the ongoing onslaught of external pressures can take a serious toll. In fact, the toll can be so subtle you don’t realize it’s happening. If you find yourself sinking into what feels like quick sand, stop and take action. You don’t have to go down for the count. Stressors you can’t control don’t have to control you or even hurt you. But without intervention, you may find it all gets to be too much.
Take Janeen and Carole, for example:
Janeen and Carole were neighbors and had been friends for years. They enjoyed shopping together, stopping for coffee and pastries, or splurging on Italian food at their favorite white cloth restaurant. They were both upbeat single empty nesters and reveled in their freedom once their grown children built lives of their own.
Carole was the more practical of the two, and Janeen was the more spontaneous, but oh, they had such fun together.
As the pandemic emerged, and as surprising as it was, they didn’t expect it to have that much of an impact on their lives because they were both already so content doing things at home — together or individually. And they did, whether it was a craft project, or constructing a puzzle, or playing cards.
However, with the spread of the pandemic, they each knew more and more people who became ill from it. Of course, Janeen and Carole were diligent with all the precautions including masks, gloves, hand sanitizer, and social distancing. Still, they knew someone who was critically ill with the coronavirus, and while she survived, it was pretty scary.
Then Janeen learned that a life long friend of her family had died in the hospital from COVID.
Three weeks later, the brother of her co-worker also died. Both losses hit her hard. Then a cousin also died. Of course, they were reading about someone well-known who also died every day or two. The losses of dear people in this pandemic were unexpected and heartbreaking.
You know that feeling when something so alarming happens that you hear about it in the news…but you never think it will happen to anyone you know..? Exactly. The alarming aspects of this disaster were getting too close to home for these friends. And in spite of the upbeat friendship Janeen and Carole shared, they discovered stressors you can’t control weren’t as easy to push aside when they plunder your personal life and those you hold dear.
That Last Straw that Can Break a Camel’s Back…
Finally, Carole’s sister Greta called and the tone of the conversation turned sour, then bitter…until her sister attacked her utterly unexpectedly. She attacked her political beliefs, her faith, and her family. By the time Carole ended the call, she was shocked and deeply wounded. Devastated. She felt betrayed at the deepest level. Carole trusted her sister. She respected her opinions and felt support from her so fundamentally, that she had always been confident they would never treat each other with disrespect.
Carole told herself her sister was just having a bad day. Or maybe the stressors of everything happening were wearing down Greta, too..? At any rate, Carole felt silly that she was so hurt by the things her sister said. She’d never been one to be so touchy with her family, to have her feelings on her cuff.
But… for Carole, it was as if the clouds had covered the sun. The shades on her life had been drawn. And the light that had normally shone on her days disappeared. Carole didn’t understand what was happening to her. But the color in life had turned shades of gray.
There was no reason to take her sister’s verbal assault so personally. But still, her outlook deteriorated. She couldn’t seem to help it.
She read on the internet that depression seemed to be on the rise with COVID…and she wondered if that was happening to her for some inexplicable reason. It was as if she had lost her zest for life. As the days and weeks passed, she realized she didn’t really care what her sister did…or what Janeen did. She felt so deflated she didn’t want to get out of bed.
So she didn’t.
Carole’s highly energized and determined personality went limp. Sad. Empty.
As days, weeks, and months passed, Carole knew she had become withdrawn. But she didn’t care. Nothing seemed to matter.
Eventually, she realized she didn’t see any reason to keep living. Her children were living their own lives now, and she was no longer needed. She thought sometimes about how the end of life would come for her. Would she just not wake up one day?
Or develop a catastrophic disease? Then she realized she didn’t really have to wait…
So she wondered how hard it would be to just put a STOP to her life. To be released from the phenomenal stress she’d lived with.
Janeen checked on her regularly, but Carole tried to end those contacts quickly. She just didn’t want to talk, visit, or exert any energy at all. She wished she could just sort of fade away.
Above all, though, she knew she didn’t want to do anything that caused her family pain… Still, she continued to think about it…
When we look back in history to extremely stressful situations, we see how severe stressors can lead to suicide in masses of people. For instance, the stock market crash of 1929 for example, illustrates how extreme stress contributed to psychiatric crises for countless people.
This winter — 2021 — has been a “perfect storm” of circumstances with the combination of the COVID-19 pandemic, flu season, the COVID variants, remote learning at home for kids, remote working from home, (where stressed parents try to do their job while supervising their children in the same space) and now a historical series of severe arctic storms sweeping from coast to coast, with snow, sleet, and ice causing life threatening traffic pileups, a break down in transportation of goods and services, preventing communities from having what they need… plus a presidential election and an impeachment.
This is proving to be the most stressful, crisis-ridden winter this nation has seen in a very long time. And everyone is facing stressors they can’t control.
And all this stress is dangerous.
Some people have taken every precaution to try to maintain health and safety, and to help contain the fallout of each of these crises. Others have all but thumbed their noses at the need for precaution, and so many others have fallen somewhere in between.
Most people are relatively resilient, and will weather whatever is thrown across their path. But if major stressors are tossed at them day after day, week after week, month after month…eventually they’ll need some sort of relief…a break to recover.
In this particular winter of 2020/2021, we may find ourselves isolated or quarantined. But we still need that break. We need to reach out for relief.
By building a network of people we look forward to talking and laughing with online. Or writing for self-fulfillment and to draw interaction from others, or cooking meals and delivering them to neighbors nearby.
We all need to give. We all need to receive. And we all need feedback. When we give, receive, and participate in feedback…well, those are stressors we can control…so they help.
When the things we need as humans are accessible and balanced in our lives, it’s easier to maintain a certain equilibrium.
But our human needs aren’t always easy to fulfill, and as stressors pile high upon us, we may need more to help us survive.
We may need a treatment to help restore equilibrium. These are highly stressful times for many, many people for a multitude of reasons. While we need to lean into our support system and find it’s not in place, we may need extra support.
Something that IV ketamine treatment excels at is resilience. And resilience chases away the clouds of disillusionment and despair. It helps you bounce back after disappointment and devastation. You may have an abundance of resilience already. But if you don’t, ketamine treatment can sure restore it and arm you for what you face when you’re confronted with stressors you can’t control.
At Innovative Psychiatry, resilience is a remarkable and startling bloom we often see in our ketamine patients. After years of living in a slump, stripped of courage, patience, hope, purpose…to see the same person develop a bright and open countenance, to hear the laughter in his voice, the hope, the confidence…the warmth; to see a life changed so splendidly makes what we do so rewarding.
While ketamine is not effective for everyone — we so wish it was! — its extraordinary impact is life-transforming for many. Neuroscience researchers continue to probe to find reasons for those it doesn’t help.
We also have protocols to ensure your safety when you come to our office for treatment. With Novaerus units in each room that remove the coronavirus from the air you breathe, and surfaces treated by Steramist, which removes 99.999% of all the virus, bacteria, and dangerous pathogens from ALL surfaces, we are diligent about keeping our air clean. We all wear masks, and keep the door locked. We’ve made so many changes… and reinvent down to the smallest details.
You can feel secure knowing that, so you can seek treatment for your depression, PTSD, social anxiety, and suicidal thinking symptoms without fear of COVID infection.
When it seems that the things in life you could always trust seem to fall around you, and the dread of it wears down your ability to try anymore, you might want to call us.
You might want to discuss your options for getting your resilience back.
And if you do, we’ll do our best to help you navigate your way through the barrage.
To find the best you to face the circumstances around you and the stressors you can’t control.
Across the country, extreme winter storms have descended upon us. Even in the Gulf states, short sleeve weather is suddenly shifting to snow. Temperatures are dropping from 70 degrees to 17 degrees.
And the gray skies that bring snow, also contribute to Seasonal Affective Disorder. Gray on the outside can turn some people gray on the inside. And typically, about 5% American adults suffer depression symptoms this time of year only. These sufferers feel fine the other seasons of the year. But something about gray skies, less light, and snow trigger sadness. Which is why they call it SAD. Call it seasonal affective disorder or SAD or any other name. It still feels like depression.
Symptoms include sadness, low energy, fatigue, weight gain or loss, and reduced interest in things they used to enjoy.
And specifically, symptoms begin in late fall…and subside in spring.
Sound familiar? If you’ve ever suffered from depression, you probably recognize these symptoms. Because this disorder that’s associated only with winter is aseasonal depression.
Some believe that the longer nights and shorter days interfere with your body’s internal clock. And that can result in changes in the brain. So using natural light and light boxes can help.
But this year… Katie Bar the Door!!
This year all bets are off. Due to the extra strain and anxiety caused by the COVID pandemic, plus the addition of flu season, the pandemic is causing anxiety and depression on its own. As the infection and death rate have grown, there is also SAD pulling people into darker places.
Social distancing reduces social interaction. Increased stress arises from financial difficulties, employment layoffs and remote learning. That cooped up feeling from being inside the house all day…as well as heightened alert about health… These stressors can cause brain cell changes that can lead to depression.
It goes without saying that so much time in the house because of COVID means less exposure to natural sunlight. You see where this is going.
SAD + COVID precautions + Flu season = Increased risk of depression and anxiety
We’re not making light of the bombarding risks facing you this winter that threaten your wellbeing. On the contrary, recognize that this season holds a unique storm of confusing symptoms. These symptoms can emerge in your health and your wellbeing.
The symptoms can be from depression you’ve had all year, or the result of COVID’s strain, or if it only happens this time of year it could be from SAD…. That’s why they call it seasonal affective disorder.
And being informed and familiar can help protect you from confusion and overwhelm if a tangle of symptoms should emerge in you or your family.
There are things you can do. For SAD, light therapy is helpful for lots of people.
Symptoms of SAD intersect with symptoms of major depressive disorder, and some of the symptoms can also be found in cases of flu and COVID, like fatigue.
So don’t be too unnerved if you find you have feelings of a deep dread, or increased agitation, or nervousness. If at all possible, this is not the time for controversial conversations about politics or religious differences. You may not realize the the underlying agitation or fear you feel may actually be stimulated by the pandemic and its restrictions, rather than the subject that seems so upsetting.
Families have been thrown into upheaval and even split apart by this dread and agitation that only began since the COVID crisis. Keep your relationships shielded and safe.
This is a great time for finding ways to reassure the people in your world, to find light-hearted discussions, and to maintain a sense of humor. This is a time for helping the people around you to maintain stability and get through this, rather than allowing controversy to up-end those already on shaky ground.
Find Healthy Ways to Bring Light Into Your Life
Seek out healthy and productive ways of occupying your thoughts, and avoid those counter to your wellbeing, such as alcohol and substance use. Do your best to find ways to brighten your family and friends with online games, painting projects, sewing and knitting (not just for the ladies now… you guys are missing creative fun if you don’t try it!), and all the ideas you can come up with that will get everyone talking and laughing in front of the computer screen!
If you’ve experienced SAD in prior years, this year may be more severe, so seek natural light as often as possible… You can call it seasonal affective disorder or just depression… either way, there’s hope.
And if you do have depression symptoms that don’t respond to medication, there’s hope. If the medication that has been effective for years has suddenly become ineffective over the past year, hang on. IV ketamine treatment just may make the difference you need.
We have patients who may require a few more than the traditional six infusions, who recover so dramatically they haven’t needed more. That’s not to say those same patients might not eventually need another infusion eventually. They know to watch for the signs.
But sometimes people read articles and misunderstand about how ketamine treatment works. They think they have to keep getting infusions every couple months, or they read that ketamine treatment can’t really last.
Broad assumptions should be avoided when it comes to treatment in the brain. Results vary among different people, and as we often remind our readers, ketamine doesn’t work for everyone. But when it works, it can work dramatically well. And it can do a transformative work in most patients who are candidates for it.
Whether You Call It Seasonal Affective Disorder or Something Else, You Might Want to See what Ketamine Treatment Can Do for You
We also invite our ketamine patients to ask their healthcare team to collaborate with us as we deliver the infusions and they can follow up with any needed therapies.
Also, for the sake of safety, we have a protocol for patients who come to the office that involves special instructions, mask wearing, and special safety precautions.
To this end, we’ve installed technology that destroys viruses including the COVID and flu viruses, as well as bacteria and molds in the air and on surfaces. This means that when we open the door for your appointment, you can come inside for treatment with confidence, knowing you’re safe.
Don’t wait.
You may call it seasonal affective disorder…or SAD… or major depression or other affective disorders, but if they’re not helped by medication, call us.
This is a tough winter, and these intensive winter storms aren’t making it any easier. Reach out for resilience.
Your remission is what we live to help you achieve.
1Internal Medicine & Addiction Medicine, Waban, MA, United States
2Consultant-Ketogenic Diet Therapy LLC, Elm Grove, WI, United States
3Innovative Psychiatry, South Windsor, CT, United States
4Center for Neural Sciences, New York University, New York, NY, United States
5The Neuroscience Institute, NYU Langone Medical Center, New York, NY, United States
6Center of Excellence in Eating and Weight Disorders, Icahn School of Medicine at Mount Sinai, New York, NY, United States
Background: Chronic anorexia nervosa is a tragic disease with no known effective pharmacological or behavioral treatment. We report the case of a 29 year-old woman who struggled with severe and enduring anorexia nervosa for 15 years, and experienced a complete recovery following a novel treatment of adopting a ketogenic diet followed by ketamine infusions. Her remission has persisted for over 6 months.
Case Presentation: At age 14.5, the patient embarked on an effort to “eat healthy.” She quickly lost control of the dieting, developed associated compulsions and obsessions about food, body dissatisfaction, emotional lability, and lost nearly 13.6 kilograms (30 pounds). She was hospitalized for 6 weeks, and while she regained some weight, she did not attain full weight restoration. For 15 years, she continued to eat in a restrictive manner, exercise compulsively, and have intermittent periods of alcohol dependence. Nevertheless, she always hoped to get well, and at age 29, she began a novel treatment for anorexia nervosa.
Conclusions: This is the first report of a ketogenic diet used specifically for the treatment of anorexia nervosa, followed by a short series of titrated IV ketamine infusions leading to complete remission of severe and enduring anorexia nervosa, with weight restoration, and sustained cessation of cognitive and behavioral symptoms, for 6 months. Although these treatments were used sequentially the relationship between these modalities, and possible synergy, is unclear, and deserves further study. Complete and sustained remission of chronic anorexia nervosa is quite rare, and the novel use of a ketogenic diet and IV ketamine treatment in this potentially lethal condition suggests avenues for further research, and hope for patients and their families.
Introduction
Anorexia nervosa (AN) is a severe disorder characterized by self-starvation, hyperactivity, anxiety, body dissatisfaction, and emotional dysregulation that usually begins in early puberty, and affects females more frequently than males. When weight restoration is the only criteria measured, rates of 60% recovery are often noted, but when cognitive recovery is included, the results are more discouraging (1–3). Severe and enduring anorexia nervosa refers to cases that have persisted for at least 3 years, and are resistant to intervention. It is a tragic disorder with no consistently effective pharmacological or behavioral treatments. The mortality rate is estimated to be ten times higher than that of the general female population, due to medical complications of self-starvation, and suicide (4). We report a case of severe and chronic AN treated successfully by adopting a ketogenic (KG) diet for 3 months followed by a series of intravenous ketamine infusions.
Emerging data suggest that disturbances in lipid signaling may underlay some of the core pathology of anorexia nervosa (5–7) and that chronic starvation may promote a type of metabolic hibernation in patients (8) that requires normalization of lipid signals to resume premorbid metabolic and central nervous system functions. A KG diet is a high fat, low carbohydrate medical diet, that leads to increased fatty acid oxidation for cellular energy, which in turn results in increased ketone body production. Ketones are produced in the liver whenever fat metabolism increases over carbohydrate metabolism; such as fasting, post-exercise, neonatal period, and KG diet, as well as during pathological states such as starvation or uncontrolled diabetes mellitus (9). Ketones easily pass the blood brain barrier and become the brains’ major energy source. This change in metabolic fuel from glucose to ketones leads to a myriad of changes in central nervous system neurotransmitters such as adenosine and gamma-aminobutyric acid (GABA), as well as neuropeptides such as leptin, adiponectin, and growth hormone-releasing peptides (10). As far as we know, this is the first publication describing the use of a KG diet for patients with AN.
In addition to dietary disturbances and potential metabolic disturbances, psychiatric symptoms such as anxiety, obsessive-compulsive disorder, depression, and addiction are frequently observed among individuals with AN (11). Ketamine has emerged as a novel treatment for treatment-resistant mood disorders, particularly those with suicidal ideation (12, 13). As far as we are aware, there is only one published study of ketamine infusions for AN, and it was encouraging (14).
We report the case of a 29 year-old woman, with chronic severe AN who had an excellent response to adopting a ketogenic diet and undergoing ketamine infusions.
Case Presentation and Clinical Assessment
The patient was a 29 years old single woman, diagnosed with AN at age 14.5, and intermittent alcohol dependence beginning at age 18. She was not in active psychiatric treatment, although she saw a supportive therapist episodically and attended Alcoholic Anonymous meetings at least once/month. She had been abstinent for 15 months, and was eating with many restrictions—preferring to eat by herself and use a napkin rather than a plate, eating only ice cream for days at a time, and excessively using non-nutritive low calorie sweeteners. She exercised daily and compulsively, usually spending 2 h at the gym. Her weight had been stable at 56.8 kg (125 lbs) for several years. Recognizing she was living a very limited life, she decided to try a novel treatment, and worked closely with an internist who was knowledgeable about eating disorders, who is the first author.
The patient was the product of a normal pregnancy and delivery and raised in an upper middle class home by parents who are both attorneys. Her older sister was very concerned with her own appearance. Family history was significant for a paternal grandmother who was obsessed with “being very slender” all her life, though was never given a psychiatric diagnosis. The patient’s mother was diagnosed with an anxiety disorder and was prescribed citalopram.
At an early age, the patient was identified as athletic, artistic, and excelled academically. Her parents noted that she had “compulsive tendencies’ such as “grinding erasers” and wanting her possessions to be lined up symmetrically, but this never reached the level of clinical concern.
At age 14.5, while at a sleep-away camp, she began a diet, with the aim of “eating healthier” with other girls in her bunk. When summer ended, she continued her diet. Her parents slowly became aware of a change in her mood and behavior, from a happy child to a sullen and angry teenager. They initially attributed this to the “onset of adolescence” but when her weight loss became more obvious, she was evaluated by her pediatrician, and was referred to an outpatient eating disorder clinic, where she ate 3 dinners/week. She also had weekly individual supportive therapy, and weekly meetings with a nutritionist. Her parents also saw a therapist separately. Her weights are summarized on Table 1; prior to illness she weighed 61.1 kg (136 lbs); height 1.62 meters (5’4”) with a Body Mass Index (BMI) of 23.3.
Twelve months into the course of her illness, she had a grand mal seizure. At the time, her weight was 43.5 kg (96 lbs) with BMI of 16.5, and her treatment was changed to incorporate Maudsley treatment in which the parents are actively taught to re-fed the child (15). She was resistant, and meals were rarely successful; after 6 months of out patient treatment she was hospitalized for 15 days followed by 30 days of “partial hospitalization.” On admission to the inpatient unit, her weight was 50.8 kg (112 lbs.) with a BMI of 19.2. Her pulse was 80 sitting, rising to 103 standing, and her blood pressure was 94/60 sitting; and 110/82 standing. The remainder of the exam was normal as were her electrolytes, and kidney and renal function tests, and complete blood count, MRI, EEG, and EKG. A bone density exam showed mild osteopenia of the hip and spine. She had had a normal menarche age 13, but had been amenorrheic for 7 months. She denied binging, purging, laxative, or diuretic abuse and was given the diagnosis of anorexia nervosa restricting type. She was discharged to home after attaining a weight of 54.4 kg (120 lbs.) with a BMI of 20.6.
She returned to high school, yet she never regained friendships she had prior to the hospitalization, and remained dismissive of her parents’ efforts to supervise her eating. Her weight generally hovered near 54.5 kg (120 lbs.). She started college several times, and dropped out several times, but eventually graduated from an excellent university. Over the next 8 years, she had three month-long admissions to alcohol & drug rehabilitation programs. She worked as a recovery coach in several wilderness rehabilitation programs, and began graduate school.
The only medications she was prescribed were lamotrigine for six months following the seizure, and lisexamfetamine dimesylate (Vyvanse).
At age 29, on physical exam, she appeared fit and well. Her BP was 120/72 and pulse 50, without orthostatic changes, and her weight was 56.7 kg. (125 lbs). Her physical exam was normal, as was her complete blood count, electrolytes, liver and kidney function tests. She was coached by an experienced KG nutritionist on ways to prepare high fat, low carbohydrate meals and smoothies, and encouraged to eliminate non-nutritive sweeteners. The goal was to induce a stable degree of ketosis, following a liberal KG diet with a 2:1 to 1:1 ratio of fats: carbohydrates + protein in grams. While we anticipated it might be difficult for her to eat fatty foods, as it is known that individuals with AN avoid high calorie foods (16), she found it relatively easy.
● “The whole time I was anorexic, I ate my safe foods, and there were not many: Lots of Splenda®, frozen yogurt, zucchini, eggplant and coffee. I only ate such a ridiculously limited amount of food, that the logistics of switching to keto were not that hard – when you think you want x, have y instead. If you have three x’s and that’s it, then have three y’s, and for me the ketos were bacon, eggs, cheese avocado, Medium Chain Triglyceride (MCT) oil”
Initially, she varied between strictly following the KG diet and being lax, but gradually found she was gaining insights into the anorexic “voice”, and it became easier to follow the diet and remain in ketosis.
● “Until now (KG), I ate sweetener with everything. I used to put Splenda on broccoli.”
● “I now consider myself to have a sugar allergy. When I eat avocados or bacon and eggs, the “voice” is softer, if I eat sugar I feel euphoric, but the euphoria has feelings of panic.”
She measured breath acetone levels with a portable breath monitor, 2–3 times/week. Breath acetone levels are scored qualitatively from 0 to 6, and she was at 2 or 3 (mild-medium range) when she was on the KG diet.
After 3 months on the diet, she reported she was “30-40% better, but was still troubled by anorexic compulsions.” She was referred for ketamine infusions. She underwent comprehensive evaluation, and met DSM-V criteria for anorexia nervosa, restricting type, and major depressive disorder, recurrent, moderately severe, with Patient Health Questionnaire-9 (PHQ-9) of 13 (17). She began treatment with racemic IV ketamine at dose of 0.75 mg/kg (42.68 mg), in 30 cc 0.9% normal saline infused over 45 min in a private room with dimmed lights, sound machine, using an eye mask. Pulse, blood pressure, respiration, O2 saturation, and cardiac waveform were monitored continuously throughout her infusion and showed expected variations in pulse and blood pressure which did not require intervention. Dissociation was present, as evidenced by patient report of feeling “out of my body” and “seeing things in layers,” and clinical observations. She displayed decreased verbal fluency and mild 1-2 beat end-gaze nystagmus during treatment, which resolved completely. She developed mild nausea following her first infusion. There were no other reported or observed side effects during treatment. All treatment-emergent side effects dissipated within 20 min. Within one hour of her first infusion, she felt the anorexic voice was weakening, and she had more ability to “be herself.” PHQ-9 dropped to 6. She then had three more IV ketamine infusions over the next fourteen days, at doses titrated to 1.0 mg/kg, 1.1 mg/kg, and 1.2 mg/kg to achieve and maintain dissociation during infusion. Each infusion was preceded by ondansetron 4 g sublingual and she denied nausea during or after these infusions. Her response was dramatic and occurred after the 4th infusion.
● “I know this sounds ridiculous, but I am no longer anorexic. I had so many rules I didn’t even know them. But they are gone. I can exercise because it feels good. It isn’t that I have to. I can stop when I want to.”
Notably, her PHQ-9 dropped to 6 after her first treatment, and to 2 following her third infusion.
Follow Up
She has continued to feel free from the intrusive AN obsessive thoughts, rigid AN rules, and compulsive behaviors, and to explore a fuller life, and is now over 6 months post ketamine infusion. She continues to eat a KG diet and her weight has inched up to 61.3 kilograms (136 pounds), the weight when the disease took hold at age 14.5. When she weighs herself now she notes:
● “I really didn’t know how I would feel getting on a scale and looking at my weight. Now, I am so relieved. I think I do not CARE about the number because I can SEE myself now in the mirror, so the number on the scale is ‘like’ ONE source of information, but not the ONLY one. I think 136 pounds is fine and I LOVE the way I look”,
Following treatment, she sees a therapist weekly for supportive psychotherapy, although during the COVID-19 pandemic visits have occurred by telemedicine. She checks her own weight every few weeks when she visits her cousin’s apartment where there is a scale, and it has been stable at her premorbid weight of 61.8 kg (136 lbs).
Patient Perspective
“All these years, I was still in there watching, waiting, and hoping to escape. Every single interaction now is a new freedom.”
She is very supportive of this publication and hopes this treatment will be studied to determine if it is effective for other patients who suffer, as she did.
Discussion
This is a striking case report of an unusual combination of a ketogenic diet and a short series of titrated ketamine infusions in a patient with severe chronic AN of 15 years – modalities that have a rational medical justification, but have never been used clinically for this disorder, or in this patient population. This resulted in a surprising and long lasting complete remission which has continued despite the stressors of living in New York City in the midst of the COVID-19 pandemic. The strength of this case report is that it offers an innovative approach to chronic AN, a disorder which is exceedingly resistant to treatment and associated with an increased risk of death.
KG diets for AN have been roundly dismissed by eating disorder experts, and with the exception of an early study in 1998, ketamine has not been reported as effective in AN. Thus, it is critical to consider the context of how this treatment sequence evolved for this patient.
The impetus for this treatment arose when the patient was presented with an etiological theory of AN, known as Adaptation to Flee Famine Hypothesis, which frames the genesis of AN as metabolic rather than psychological (18). This resonated deeply with the patient, as she often had felt she was battling invisible forces. Seeing her symptoms as the result of distorted physiological signals and offering a metabolic solution was powerfully motivating. Explaining that there was an animal model for AN that replicated many of its symptoms, was also empowering, as it countered the narrative that she was somehow “choosing” this disorder in order to exert “control” over her life. These psycho-social constructs, which she had heard many times in rehabilitation centers, had never rung true for her, and had also burdened her with guilt for “causing her own illness.”
The Adaptation to Flee Famine Hypothesis posits that it would have been evolutionarily advantageous to a nomadic tribe if some members acted uniquely when presented with a state of food scarcity or famine. If these individuals could deny hunger, dismiss their obvious body inanition, act as if they were just fine, and engage in hyperactive running long distances, they might lead the tribe to better hunting grounds. These are precisely the behaviors seen in adolescents with AN.
The activity-based-anorexia rodent model involves housing a rodent in a cage with a running wheel, and decreasing the food supply slightly (19). Some animals, often female and adolescent, will increase running and reduce eating drastically, thus replicating aspects of human AN. The model requires both stimuli of decreased food supply plus unlimited access to a running wheel.
Advising the patient to adopt a KG diet was prompted by two factors. First, two studies employing an activity-based-anorexia model demonstrated that a KG diet rescued the animals from self-starvation (20); and a high-fat diet (although not ketogenic) prevented the animals’ self starvation (21). Secondly, the KG diet has an impressive record of safety and efficacy for treating seizure disorders in children, and has been used continuously since the 1920s (22). It is an emerging therapy for treatment of other neurological and psychiatric disorders such as Parkinson’s, early Alzheimer’s, and bipolar disorder (23). Thus, since it is generally safe and effective for other neurological disorders, it might also prove effective for AN, especially since AN has been shown to be genetically linked with abnormalities in fat metabolism (6).
There are known side effects of the KG diet which are occasionally observed in patients treated for seizures. These include weight loss, constipation, nephrolithiasis, and hypoglycemia. These effects are seen most often in children who are on multiple anti-seizure medications and are often physically compromised. Fortunately, this patient did not experience any of these symptoms and her weight increased as she ate with more freedom. The patient was at a stable weight and the only medication was lisexamfetamine dimesylate (Vyvanse). Furthermore, a more rigid ketogenic diet of 4:1 fat: protein plus carbohydrate diet is often employed for patients with seizures, while the diet employed in this case was a more liberal diet of 2:1 or 1:1 which may have mitigated some of the possible side effects of the KG diet.
It is unknown whether the positive results from the KG diet arm of the treatment were due to adopting a KG diet, or if simply adopting a high fat diet without the carbohydrate restriction required for ketosis would have been effective. We believe it was the ketogenic nature of the diet because the biochemical changes seen with ketosis are different from those seen with increased fat. A recent article testing a ketogenic diet in humans, and also transplanting the microbiome into mice, noted that the microbiome responds differently to a moderate fat diet, a high fat diet that is not ketogenic, and a high fat/low carbohydrate that is ketogenic (24). This is an area of active research.
If the patient had been pleased with the results of the KG diet alone, the treatment would have stopped at that point. She reported the symptoms of AN were “30-40% improved but she was still troubled with anorexic compulsions. Thus the second “arm” of the treatment began—ketamine infusions. The addition of ketamine treatment in this case was also based on studies on the activity-based-anorexia model, plus one very interesting, and overlooked case series report from 1998.
Experiments with the activity-based-anorexia model found that individual rodents vulnerability to self-starvation correlated with levels of N-methyl-D-aspartate (NMDA) glutamine receptors in the dorsal hippocampus (19). Since ketamine is a well known antagonist to NMDA glutamine receptors, an elegant experiment examined whether injection of ketamine on day 2 when the animal had started to self-starve and hyper-exercise could alter the behavior (25). As predicted, those treated with ketamine ate more, exercised less, and were resilient to the self-starvation when they were re-exposed to the paradigm, compared to those treated with placebo.
Very similar reasoning was described for the rationale of a study from Cambridge, England, published in 1998 in which Mills et al. treated 15 patients with chronic severe AN with a series of ketamine infusions (14). Significant prolonged improvement was reported in 9 patients. Some of the responses resembled the dramatic changes noted in this case report.
It is difficult to determine the doses of ketamine administered in this report because the authors describe that infusions were delivered at 20 mg/h for 10 h using doses “similar to that used to produce analgesia” but exact doses were not stated. Furthermore all patients in this series were prescribed an opiod blocker to “ensure they remained conscious”.
We approached the ketamine arm of the treatment cautiously because the patient had struggled with alcohol dependence, substance abuse is common in patients with AN, and ketamine is a drug that is recreationally abused. A recent study, pooling data from 5 clinical trials found no evidence of serious side effects from a single infusion of ketamine for clinical depression, and ketamine was not associated with increased abuse (26). Many patients reported feeling “loopy” or “dissociative” during the infusion, but this passed rapidly. While this study is promising, racemic ketamine infusions for psychiatric disorders remains off-label, and issues of optimal dose, duration, titration, and number of infusions needs further research. In AN, these questions deserve further investigation and warrant controlled trials. This patient did indeed experience dissociation during her infusions, which she found was part of its therapeutic effect.
Although the efficacy of KG diet for seizure disorders, and ketamine infusion for severe treatment resistant depression has been clearly demonstrated, the mechanisms of actions of both agents are not well understood. It is notable that both ketamine and KG diet have been shown to intimately affect brain-derived neurotrophic factor (BDNF), gamma-Aminobutyric acid (GABA), and N-methyl-D-aspartate (NMDA) glutamate receptors which are the same molecules affected in the activity- based-anorexia model (27, 28). It is possible that the KG diet and IV ketamine act synergistically, with the KG diet “priming” the response to ketamine. This requires further study.
There are several important limitations to this report and to the generalizability of the findings. Most importantly, this is a single case report and further study is needed. Secondly, standardized eating disorder rating scales were not used to monitor progress. This is because this is a report about a clinical experience with a patient used to monitoring her own eating and activity levels by journaling; it was not organized as a clinical trial. There are no eating disorder scales that have been validated for used with ketamine treatment. Third, this treatment paradigm essentially involved three modalities, and not just two treatment arms: first the patients adoption and reconsideration of AN as a disorder whose symptoms are predominately metabolically driven, which was an enormous paradigm shift for her; secondly adopting the KG diet and contextualizing ketosis as helpful for her brain rather than as a weight loss or weight control method for her body; and third IV ketamine infusions at a dose and titration schedule not previously reported. The fact that this sequential treatment resulted in complete and sustained remission of this patient’s severe AN thoughts and behaviors was unexpected. Furthermore, her remission has persisted despite extreme stressors, social isolation, work restrictions, and treatment disruptions during the COVID-19 pandemic in NYC. At his point it is not possible to state which modality was essential, or which had the most important therapeutic benefit, if both ketogenesis and ketamine are necessary and synergistic, or if the treatment would have been as effective if the KG diet were initiated with ketamine when ketamine infusions began instead of preceding them by several months. It is possible that ketamine infusions alone would have been effective. Future studies are necessary to address these questions, and to address optimal KG diet ratios and optimization of ketamine dose, duration, and frequency.
Conclusions
There remain many unanswered questions about the generalizability of these findings to other patients with AN. Yet, the medical plausibility of this treatment and the dire prognosis of chronic anorexia nervosa, suggest that both the KG diet and ketamine treatment warrant further study in this patient population towards the goals of restoring weight, normalizing cognitive and emotional functioning, and improving quality of life. It is hoped that this report will stimulate this research.
Data Availability Statement
The original contributions presented in the study are included in the article/supplementary material; further inquiries can be directed to the corresponding author.
Ethics Statement
Ethical review and approval was not required for the study on human participants in accordance with the local legislation and institutional requirements. The patient provided her written informed consent to participate in this study. Written informed consent was obtained from the individual, for the publication of any potentially identifiable images or data included in this article.
Author Contributions
All authors contributed to the article and approved the submitted version. BS orchestrated the treatment and wrote the first draft of paper. BK coached the patient on the ketogenic die and edited the paper. LC performed a comprehensive evaluation of the patient, treated the patient with ketamine infusions, and edited the paper. CA performed the studies on activity-based-anorexia, kept the authors informed of her studies, and edited the paper. TH was the primary medical provider 15 years ago when the patient first became ill, continued to consult regarding her care over the years, and edited the paper.
Conflict of Interest
Author BZ-K was employed by the company Ketogenic Diet Therapy LLC.
The remaining authors declare that the research was conducted in the absence of any commercial or financial relationships that could be construed as a potential conflict of interest.
References
1. Murray SB, Loeb KL, LeGrange K. Treatment outcome reporting in anorexia nervosa: time for a paradigm shift? J Eating Disord (2018) 6:10 . doi: 10.1186/s40337-018-00195-1
2. Eddy KT, Tabri TN, Thomas JJ, Murray HB, Keshaviah A, Hastings E, et al. Recovery from anorexia nervosa and bulimia nervosa at 22-year follow up. J Clin Psychiatry (2017) 78(2):184–9. doi: 10.4088/JCP.15m10393
3. Fichter MM, Quadflieg N, Crosby RD, Koch S. Long-term outcome of anorexia nervosa: results from a large clinical longitudinal study. Int J Eat Disord (2017) 50:1018–30. doi: 10.1002/eat.22736
6. Watson HJ, Yilmaz Z, Thornton LM, Hubel C, Coleman JR II, Gaspar HA, et al. Genome-wide association study identifies eight risk loci and implicates metabo-psychiatric origins for anorexia nervosa. Nat Genet (2019) 51(8):1207–14. doi: 10.1038/s41588-019-0439-2
8. Scolnick B. Hypothesis: Clues from mammalian hibernation for treating patients with anorexia nervosa. Front Psychol (2018) 9:2159. doi: 10.3389/fpsyg.2018.02159
10. Giordano C, Marchio M, Timofeeva E, Biagnin G. Neuroactive peptides as putative mediators of antiepileptic ketogenic dies. Front Neurol Rev (2014) 29(5):63. doi: 10.3389/fneuro.2014.00063
12. Fond G, Loundou A, Rabu C, Macgregor A, Lancon C, Brittner M, et al. Ketamine administration in depressive disorders: a systematic review and meta-analysis. Psychopharmacol (Berl) (2014) 231(18):3663–76. doi: 10.1007/s00213-014-3664-5
13. Calabrese L. Titrated serial ketamine infusions stop outpatient suicidality and avert ER visits and hospitalizations. Int J Psychiatr Res (2019) 2(6):1–12.
16. Schebendach JE, Mayer LE, Devlin MJ, Atia E, Contento IR, Wolf RL, et al. Food choice and diet variety in weight-restored patients with anorexia nervosa. J Am Diet Assoc (2011) 111(5):732–6. doi: 10.1016/j.jada.2011.02.002
18. Guisinger S. Adapted to flee famine: adding an evolutionary perspective on anorexia nervosa. Psychol Rev (2003) 110(4):745–61. doi: 10.1037/0033-295X.110.4.745
19. Aoki C. Synaptic changes in the hippocampus of adolescent female rodents associated with resilience to anxiety and suppression of food restriction-evoked hyperactivity in an animal model for anorexia nervosa. Brain Res (2017) 1654(PtB):102–15. doi: 10.1016/j.brainres.2016.01.019
21. Brown AJ, Avena NM, Hoebel BG. A high fat diet prevents and reverses the development of activity-based anorexia in rats. Int J Eat Disord (2008) 41(5):383–9. doi: 10.1002/eat.20150
22. Freeman JM, Kossoff EH. Ketosis and the ketogenic diet.2010: advances in treating epilepsy and other disorders. Adv Pediatr (2010) 57(1):315–29. doi: 10.1016/j.yapd.2010.08.003
23. Strafstrom CE, Rho JM. The ketogenic diet as a treatment paradigm for diverse neurological disorders. Front Pharmacol (2012) 3:59. doi: 10.3389/fpharm.20012.00059
24. Ang QY, Aleaxander, Newman JC, Tian Y, Cai J, Turnbaugh PJ. Ketogenic diets alter the gut microbiome resulting in decreased intestinal Th17 cells. Cell (2020) 181:1263–75. doi: 10.1016/j.cell.2020.04.027
25. Chen YW, Sherpa AD, Aoki C. Single injection of ketamine during mid-adolescence promotes long-lasting resilience to activity based anorexia of female mice by increasing food intake and attenuating hyperactivity as well as anxiety like behavior. Int J Eat Disord (2018) 51:1020 –1025. doi: 10.1002/eat.22937
26. Acevedo-Diaz E, Cavanaugh GW, Kraus C, Bashkim K, Zarate CA. Comprehensive assessment of the side effects associated with a single dose of ketamine in treatment-resistant depression. J Affect Disord (2019) 263:568–75. doi: 10.1016/j.jad.2019.11.028
27. Hartman AL, Gasior M, Vining E, Rogawski MA. The neuropharmacology of the ketogenic diet. Pediat Neurol (2007) 36(5):281–92. doi: 10.1016/j.pediatrneurol.2007.02.008
Anorexia Nervosa is an eating disorder that can affect people of all ages, genders, sexual orientations, races, and ethnicities. It is characterized by extreme weight loss and consequent difficulties maintaining an appropriate body weight for the height and age of the sufferer. It is not a new condition, and many historians believe there is evidence to suggest that individuals have been displaying symptoms of anorexia for hundreds or even thousands of years. Treatment plans are often tailored to the individual patient and can range from cognitive behavioural therapy, a hospital stay, psychotherapy and help from a registered dietitian. However, despite these treatments, recovery is a long process.
In this piece, we have the privilege of taking a look at a new potential treatment option for Chronic Anorexia Nervosa, from the three viewpoints – the author of a compelling research article, the Faculty Member who recommended the work, and the patient involved in the study. Let’s introduce these participants:
Barbara Scolnick is a semi-retired internist who lives in Boston, MA. She graduated from Columbia College of Physicians & Surgeons in 1977. During this time she often worked part-time in outpatient clinics and also raised 3 children.
Caroline Beckwith is Barbara’s niece and the patient in this study. She has a Bachelor’s Degree from the University of Wisconsin Madison and half of a Master’s Degree from Columbia University Teachers College. Her Anorexia and addiction ultimately made finishing this program pretty impossible.
Maria Consolata Miletta is an Associate Faculty Member for Faculty Opinions who works with Tamas Horvath to evaluate the literature relevant to their research interests. She is currently a group leader at the University of Zurich. Her main research interests are the neurobiology of anorexia nervosa and she hopes that one day she can study the condition at a single-cell resolution and begin to lay the foundation of an effective cure.
*This study was conceptualized and implemented by Prof. Tamas Horvath, Faculty Member, principal investigator and last author on the paper, and performed in his lab at the Yale School of Medicine.
What sparked your interest in researching Anorexia Nervosa?
BS: Everything changed 15 years ago when my niece Caroline Beckwith was 14 years old. Since her mother and I are identical twins, our families are very close. Caroline was funny, athletic, easy-going, and in general a pleasure to be around, until she developed anorexia nervosa, and was swallowed up, not to emerge for 15 years. Once she developed anorexia nervosa, I tried to find answers.
MM: My main research interest at the end of my PhD was the physiology of fasting: specifically, what happens to our body when we fast and how long can we? Hence I contacted Prof Tamas Horvath, a worldwide expert in the field and I moved to Yale for a postdoc in his lab. He has been studying for 25 years a family of neurons physiologically active during fasting called AgRP neurons. The hypothesis was that these neurons might be involved in the development of Anorexia Nervosa. There were some supportive data from clinical studies too. Patients suffering from Anorexia have a high level of circulating AgRP protein in the blood for example. These neurons are located in the hypothalamus, a deep region in the brain mainly involved in feeding behavior.
The project was risky but we really surprised by the results. We found that AgRP neurons, when activated in an activity-based anorexia model, modulate a complex response that involve both metabolic and behavioral changes to adapt to fasting.
What is your relationship with the study “Remission from Chronic Anorexia Nervosa With Ketogenic Diet and Ketamine: Case Report”?
BS: This entire project was dependent upon my easy access to PubMed, initially at the Harvard medical school library, and then my home computer. I used this tool to read papers of scientists who worked at different decades and disparate fields—lipid research, hibernation, brain histology. Among the influential scientists was Ralph Holman who described the skewed fatty acid profile seen in patients with anorexia nervosa. Shan Guisinger authored “Adaptation to Flee Famine” and noted that patients with anorexia nervosa and migrating mammals both engage in constant motion and minimal eating, and suggested that anorexia nervosa was a manifestation of an ancient adaptation to fleeing famine.
Discovering that an animal model of anorexia had been described since the 1960s was eye-opening. The activity-based anorexia rodent model of anorexia nervosa was based on the observation that some rodents when placed in a cage with a running wheel and subjected to a slight decrease in the food supply, proceed to hyper-exercise and reject all food, and actually starve to death if not removed from the cage. This self-starvation required both stimuli; the running wheel and decreased food supply.
”The most important message is that: Anorexia is not a choice. There is so much stigma in society for people suffering from Anorexia and this might delay getting the most appropriate treatment or even getting appropriate funding for research. Patients do not choose to starve to death.Maria Miletta, Group Leader, Department of Neonatology, University of Zürich.
I wondered if a faulty brain circuit responsible for recognizing the ambient food supply might be the underlying pathology in anorexia nervosa. One could hypothesize, that this “faulty circuit” would be asymptomatic unless the patient experienced an initially minor episode of insufficient nutrition, and then, unfortunately, it would become obvious. Hibernation is an adaptation that requires the mammal to recognize and anticipate changes in ambient food supply so I focused my reading on hibernation.
The ketogenic diet has been shown to be an effective treatment for seizure disorders since it was described in 1921. While the exact mechanism of action remains unknown, the diet causes the brain energy supply to shift from being dependent on glucose to being driven by ketones. This is a fundamental change which alters many pathways. When I found articles from 1970s, that suggested the ketogenic diet was useful in the activity-based anorexia model, I wondered why it was not tried in humans. It seemed to tie the pieces together.
MM: Currently, there is no effective treatment for anorexia. It is worrisome because it is the psychiatric disorder with the highest mortality (almost 10% according to the national institute of mental health). Actual treatment involves the restoration of the normal body weight, addressing the abnormal behaviors that promote and support this eating disorder, often a parallel treatment with antidepressants. 20% of patients will develop chronic anorexia. This study report is interesting because find a long-term strategy that can help in both managing the weight and the psychiatric symptoms (phobia to eat, compulsive behaviors). Certainly, to be considered effective, the treatment should be extended to a greater number of patients.
What were the limitations and challenges of this study?
BS: I was so excited to come up with something that might help Caroline. The disappointment was severe when no one in academia would research these ideas, and few would even entertain them. Ketogenic diets are commonly used for weight loss, so it was thought to be contraindicated. Ketamine was more palatable to the “specialists” I reached out to, but the doses considered by the academics who were treating depression with ketamine were lower than those used in the Mills study.
”It feels absolutely fantastic to be recommended by Faculty Opinions. This recommendation, which is from an excellent basic scientist has given us all a very needed boost. It is wonderful to have basic scientists and clinicians work together.Barbara Scolnick MD, Associate Investigator, Clinical Trial Ketogenic Diet/Ketamine for Anorexia Nervosa
BS: Caroline was nearing 30. She had been ill for 15 years. While her weight was nearly normal, she was consumed with compulsions to exercise and to eat in a ritualistic manner. It was not a life worth living, in her opinion. We could not wait for academics. Caroline and I talked, and walked endlessly through the streets of New York City in the pre-COVID months of 2019. Finally, we simply tried it ourselves, with the help of two great clinicians.
Beth Zupic-Kania is a nutritionist who has been treating children with seizure disorders with the ketogenic diet for a decade and graciously agreed to help us. Lori Calabrese is a psychiatrist who has used ketamine infusions to treat suicidal depression. We simply gave it a try and hoped for the best. Caroline’s response was so amazing, we were all stunned. After 4 weeks on the ketogenic diet, and 3 ketamine infusions, the anorexia nervosa related thoughts, behaviors, compulsions dissolved, and she remains in complete remission now over 12 months since the intervention.
CB: The largest, most obvious challenge, was convincing the anorexic voice in my head to allow me to eat fat. Anorexia has so many rules, but the strictest for me was to avoid high-fat food. If it was not avoidable, then I had to exercise the calories away. This voice in my head was with me every second of every day, so as I learned about the keto diet, anorexia did as well. The voice wakes up in the morning with you and starts to tell you your day. “First we’ll make coffee then we’ll do squats then we’ll do push-ups then we will go for a walk etc” ALL day. I found by eating a high fat “keto” breakfast first thing in the morning, before anything else, made anorexia quieter throughout the day. Getting myself to do this was hard, but not impossible.
There was a time in the beginning when I stopped eating keto and went back to eating what anorexia wanted me to eat (lots of walking down the streets of NYC while eating m&m’s and frozen yogurt) and this made it very clear that the high-fat diet was truly helping. I think I had to “go back” to be fully convinced that going forward with keto was the way out of anorexia. After that, eating this way became much easier.
I felt empowered every morning when I would wake up and eat bacon, eggs, avocado, and get to say “you can’t scream at me right now,” to anorexia. By the time I got the ketamine infusions, I had whole chunks of time in the day that were quiet from anorexia. It was not gone, but I could feel how much weaker it was from the diet.
MM: There is currently a growing body of evidence which shows that there is an area of the brain involved in the aetiology of anorexia, but isn’t necessarily under the conscious control of the brain. The combination of ketogenic diet and ketamine might surprisingly work in synergy with behavioral therapy because it targets these deep areas of the brain.
”The largest, most obvious challenge, was convincing the anorexic voice in my head to allow me to eat fat. Eventually, I felt empowered every morning when I would wake up and eat bacon, eggs,avocado, and get to say “you can’t scream at me right now,” to anorexia. By the time I got the ketamine infusions, I had whole chunks of time in the day that were quiet from anorexia. It was not gone, but I could feel how much weaker it was from the diet.Caroline Beckwith, Research Assistant, Clinical Trial Ketogenic Diet/Ketamine for Anorexia Nervosa
What is one thing you would like the average person to know about Anorexia Nervosa?
CB: I think people do not realize how much of a person’s life is stolen from anorexia. Looking back, I cannot believe I was allowed to go to college, live alone, feed myself, and have any chance of success.
I think the “average person” imagines someone with anorexia as a rail-thin ballerina or model. I think the easiest way to identify if someone has it is if they are clearly “following rules” that are punishing and isolating and do not appear to be in their best interest. Of course, I didn’t want to wake up at 4am and go on the elliptical machine for three hours! I just didn’t have a choice, and anorexia would not allow me to tell anyone this.
Anorexia is not a choice, or a “control issue”, or the result of some family trauma. It is completely out of control to anyone who has it, and they do not want it, but the voice tells you to keep that all a secret.
MM: The most important message is that: Anorexia is not a choice. There is so much stigma in society for people suffering from Anorexia and this might delay getting the most appropriate treatment or even getting appropriate funding for research. Patients do not choose to starve to death.
How does it feel to have your work recommended by Faculty Opinions?
BS: Absolutely fantastic. Most of the eating disorder community is absolutely shunning this idea, and I have gotten some very nasty emails, claiming it is absurd to use a diet to treat anorexia nervosa. This recommendation, which is from an excellent basic scientist has given us all a very needed boost. It is wonderful to have basic scientists and clinicians work together. As far as our pilot clinical trial, we will persist, and we will do it safely, and we will get answers.
If you’re interested in learning about research in this area, then you can read more in our Eating Disorder and Clinical Nutrition Sections. You can also follow our Associate Faculty Member, Maria Miletta.
Resilience is doing well when you shouldn’t be doing well.
— Dr. Sood, executive director of the Global Center for Resiliency and Well-being.
We’ve passed the 1-year mark of this pandemic, and it’s time to draw from our personal stores of personal strength to maintain our pace through the rest of the pandemic triumphantly. And the buzz word seems to be resilience. It’s the key to your wellbeing through COVID 2021 and beyond. Resilience means you bounce back from difficulty, recover, and more forward.
We don’t know yet if we’ll see this pandemic wind down in 4 months, 6 months, 9 months or a year. But for your own wellbeing and that of your family, your co-workers, our economy, and our community, we must develop the power to hold steady and see this challenge through.
The way we can do it is by developing and strengthening our resilience.
Since resilience is vital to our life and ability to survive emotionally, financially, in our healthy relationships, our mental and physical health, as well as our ability to handle trauma and loss… even our basic happiness… Well, we need to build it up, don’t we?
In fact, bolstering your resilience is probably the best thing you can do to prepare yourself for the challenges and changes you’ll face this year.
So How Can You Strengthen Resilience?
Each time you push past something that feels like a limit, you’re strengthening your resilience. Doing your sit-ups even though you’re not in the mood, getting up and dressing and leaving the house when you don’t feel like getting out of bed, choosing healthier foods like a salad when you’d rather have the smothered bacon fries…these are acts of resilience. They come from discipline and build resilience.
When you turn off the TV and get yourself out the door to volunteer to help others who need what you can give, your resilience grows.
It’s choosing self -control. It’s choosing to not give up. Things you do every day that build your inner reserves to call upon when the need arises.
While it’s true that some people are born with more resilience than others, it’s still good to invest in developing it. And even people who have a lot of natural resilience tend to keep cultivating it.
The challenge is to invest yourself to cultivate it when you never have before. Because by doing that, your ability to meet the challenges this year and next year will be far better than it was last year.
It’s worth the effort.
Motivation can power resilience. Getting up and doing those things you know you need to do can help you build the purpose so you can see the point of doing those things.
Practicing jazz on the saxophone for the hundredth time may feel like monotony, but it’s building skill on your instrument, as well as resilience.
How Do You Acquire Resilience?
We acquire resilience from the inside out and from the outside in. What does this mean?
Resilience comes from the rich stores inside you of self-love, self-worth, faith, hope, positivity, gratitude, courage, and conviction.
Resilience that comes from the outside in draws upon our support system, your community of people who care about you and for whom you care, your family, your friends, and your co-workers you feel connected to.
So it’s not hard to see how important it is that you choose that community carefully, guarding its impact on you, to help you build the inner strength and resilience you’ll need to draw from in difficult times. Because it’s the key to wellbeing through COVID 2021 and beyond.
Neuroplasticity Is a Wonder that Improves Resilience
As you know if you’ve been reading my posts awhile, neuroplasticity is the ability of brain cells to change or adapt. We’ve often talked about the neuroplasticity that ketamine treatment initiates.
That’s something a normal healthy brain does to help you adapt through life. But when you’re depressed, or affected by another disorder, that ability to change can become impaired.
On the other hand, when you build your resilience, neuroplasticity can function as it should.
The big obstacle is stress. We’ve talked about stress often, because it is so destructive to brain structures in the hippocampus, the prefrontal cortex, and the amygdala.
And one of the most important things you can do to bolster your resilience is to reduce the stress in your life. Because when you reduce stress, and let some time go by in a more “de-stressed” state, the brain cells in these structures can return to their normal working condition.
Then again, we also know that this stressed state can become severe enough that de-stressing isn’t enough to restore healthy function. Sometimes symptoms become so severe that suicidal thoughts begin to dominate your thoughts.
That’s when you need an intervention. Sometimes, lots of interventions. In some cases, medication can help. But since it only helps a small percentage of patients, you may need to seek out new help, other strategies, or other treatments.
When medications fail to bring you relief, and you’ve tried at least two different trials…you may want to find out if you’re a candidate for IV ketamine treatment.
That’s where we come in… because if you are a candidate, IV ketamine can be masterful at cranking up your neuroplasticity and your resilience.
And transformation can be soon to follow.
Resilience is the key to your wellbeing through COVID 2021 and beyond.
At Innovative Psychiatry, we meet people who are depressed, anxious, and sick of it all to determine if ketamine treatment might help. Many walk out at the end resilient, joyful, and full of hope.
Invest in resilience and build your inner joy to face what lies ahead. But if your efforts aren’t enough, and medications haven’t helped, call us.
If you’re a good candidate for serial titrated IV ketamine treatment, it will be our pleasure to help you through that process.
We also take your safety to heart in the midst of this pandemic and have invested in world class technology that removes COVID-19 causing virus from the air and surfaces in our offices. We use additional air sterilization processes that lay down microbarriers. And even with that presence, we still wear masks and ask that you wear them, too. We test ourselves and our staff with SARS-CoV2 PCR tests with a local DNA lab that gives us same day PCR results–incredible!–at least once a week. We also keep the door locked, to ensure that only those we’ve prescreened can enter. You can feel safe with us, and we know you need to feel safe so you can relax, receive treatment, and recover.